

Knee Arthritis
What is knee arthritis?
Knee arthritis is a condition in which the cartilage that normally cushions the knee joint gradually wears down, causing the bones to rub against one another. This leads to pain, stiffness, swelling, and a reduction in the knee's normal range of movement.
The most common form is osteoarthritis, which develops as cartilage deteriorates over time, though other forms of arthritis (such as rheumatoid or post-traumatic arthritis) can also affect the knee. Dr Varun Arora sees and treats patients with knee arthritis at all stages, from early symptoms through to advanced joint damage, across Melbourne and regional Victoria.
Symptoms
Common symptoms of knee arthritis include:
Pain that worsens with activity and improves with rest
Stiffness, particularly after periods of inactivity or first thing in the morning
Swelling around the joint
A grinding, clicking, or catching sensation in the knee
Reduced range of motion
A feeling of the knee giving way or becoming unstable
Visible changes in joint shape or alignment as the condition progresses
Causes and risk factors
IMPORTANT TO KNOW
Knee arthritis can develop for a number of reasons, including:
Age-related wear of the joint
Leg alignment (bow legs or knock knees), which overloads one side of the knee
Excess body weight, which places additional load on the joint
Joint overuse or heavy physical work
Genetic predisposition
Inflammatory or autoimmune conditions
How is knee arthritis diagnosed?
Knee arthritis is usually diagnosed from your symptoms, an examination, and weight-bearing (standing) x-rays, which show how much cartilage space is left and which part of the knee is affected. An MRI is usually not needed to diagnose arthritis. It may be used in specific situations, for example when symptoms don't match the x-rays.
Treatment options for knee arthritis
Treatment depends on your symptoms, the degree and location of joint damage, and how the arthritis is affecting your life. Dr Arora will assess your circumstances to recommend the most appropriate treatment.
Non-surgical treatment
Exercise and education. Strengthening the thigh and hip muscles, through physiotherapy or programs such as GLA:D, is the foundation of knee arthritis care.
Weight management. Losing even 5–10% of body weight can noticeably reduce knee pain.
Activity modification and pacing
Pain relief. Simple pain relief, and anti-inflammatory tablets or gels where suitable. Opioids are not recommended for long-term arthritis pain.
Bracing and walking aids. An unloader brace can help when arthritis affects one side of the knee.
Corticosteroid injections. These can give short-term relief during a flare.
These measures aim to reduce pain and improve function, and many people manage well with them for a long time, particularly in early to moderate arthritis.
What about PRP, stem cell or gel injections?
Platelet-rich plasma (PRP), stem cell and hyaluronic acid ("gel") injections are widely advertised. Australian guidelines, including the national Knee Osteoarthritis Clinical Care Standard and the Australian Orthopaedic Association, note that there isn't good evidence that they help established knee arthritis. They are also not covered by Medicare. Dr Arora is happy to discuss the evidence with you.
Surgical treatment
When non-surgical treatment no longer provides adequate relief, the right operation depends on where the arthritis is, your leg alignment, your age and your activity goals:
Knee Osteotomy. For selected younger, active patients with arthritis on one side of the knee and malalignment. The bone is realigned to shift load to the healthier side, preserving your own knee.
Unicompartmental (Partial) Knee Replacement. When arthritis is confined to one compartment, only that part is resurfaced. Healthy cartilage and ligaments are kept. It is often performed with robotic assistance.
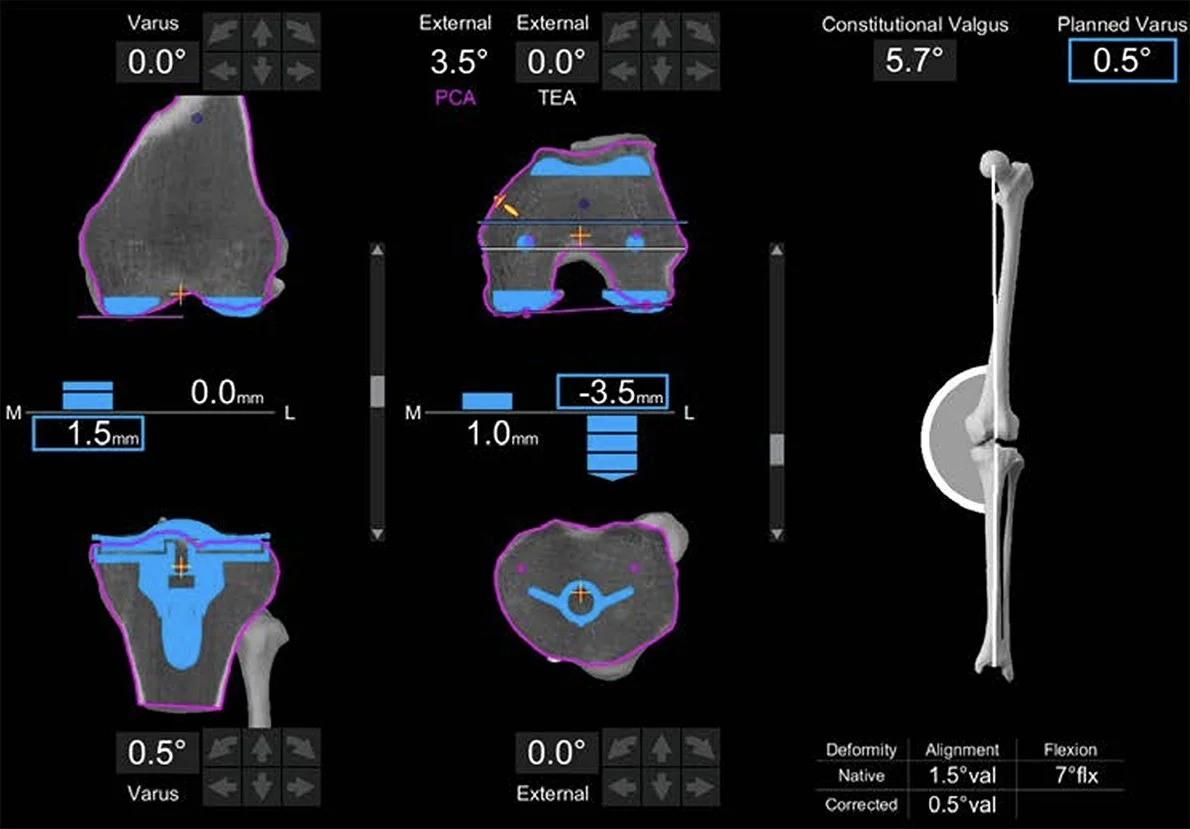
Total Knee Replacement. When arthritis affects more of the knee. Dr Arora offers robotic-assisted surgery and 3D planning with cutting guides made for your bones where suitable.
| Comparison | Osteotomy | Partial Knee replacement | Total Knee replacement |
|---|---|---|---|
| Arthritis | One side, early to moderate | One compartment | More than one compartment |
| Typical patient | Younger, active, with malaligned leg | Healthy ligaments, good movement | Most people with advanced arthritis |
| Keeps your own joint? | Yes | Partly | Joint surfaces replaced |
| More information | Knee Osteotomy | Partial Knee | Knee Replacement |
Knee arthroscopy (keyhole surgery) is not a treatment for knee arthritis and is not recommended to "clean out" an arthritic knee. In some cases it may be considered for a different problem, such as a knee that is physically locked by a torn fragment or significant mechanical symptoms. See Knee Arthroscopy.
When should I see a surgeon?
Consider asking your GP for a referral if knee pain:
Is limiting your walking, work, sleep or the activities you enjoy
Has not improved despite several months of exercise, weight management and medication
Comes with increasing leg deformity or a knee that gives way
Seeing a surgeon doesn't commit you to an operation. Many patients come for a clear diagnosis and a plan.
YOUR PATH
Knee Arthritis Frequently Asked Questions
Understanding knee arthritis
-
Arthritis can't be reversed, but its symptoms can be well managed with the right combination of non-surgical and, where needed, surgical treatment.
-
It often progresses, but slowly for many people, and symptoms can go up and down with flares. Symptoms matter more than x-ray changes when deciding on treatment.
-
Arthritis can irritate the joint lining, which produces extra fluid. Swelling often comes and goes with activity. Ice, elevation, pacing and anti-inflammatories can help.
-
Pain can briefly switch off the thigh muscles, and weakness or a worn meniscus can add to it. Strengthening exercises often help. Frequent giving way should be assessed.
-
Usually not. Standing x-rays are the best test for knee arthritis. MRI is reserved for specific questions.
-
Many people over 50 have both, and a worn meniscus is part of arthritis. Surgery for a degenerative meniscal tear in an arthritic knee generally doesn't help. See Meniscal Tear.
Living with knee arthritis
-
Yes, within reason. Exercise is one of the most effective treatments for knee arthritis. Mild discomfort that settles within a day is generally fine. Cycling, swimming, water exercise and strength training are ideal.
-
Each kilogram lost takes several kilograms of load off the knee with every step. A 5–10% weight loss often noticeably improves pain and function.
-
An unloader brace can help when arthritis mainly affects one side of the knee. A simple sleeve may help with confidence and swelling.
-
Anti-inflammatory gels and tablets (if safe for you) and paracetamol are commonly used. Check with your GP or pharmacist about what suits your health. Opioids are not recommended for long-term arthritis pain.
-
Studies have generally not shown glucosamine, chondroitin or most other supplements to work better than placebo.
Injections and other treatments
-
It can give short-term relief during a flare, often for several weeks. Repeated injections are generally limited, and are avoided in the months before surgery because of infection risk.
-
Australian guidelines don't recommend them for knee arthritis because there isn't good evidence of benefit, and they can be costly. Please discuss them with Dr Arora before committing.
-
No. Large studies show arthroscopy doesn't improve knee arthritis compared with exercise-based treatment, and it is not recommended in Australian guidelines.
Thinking about surgery
-
Surgery is considered when arthritis is significantly affecting your daily life and non-surgical treatment is no longer enough. Dr Arora can assess this with you at a consultation.
-
This depends on which parts of the knee are affected, your leg alignment, your ligaments and your activity goals. It is assessed through examination and standing x-rays. See the comparison table above.
-
Every situation is different. Some people manage for many years, while others progress more quickly. Increasing deformity, stiffness or loss of strength can make surgery and recovery harder, so regular review is sensible.
-
A 3D plan of your knee is carried out with the help of a robotic arm, while Dr Arora performs and controls every step. See Robotic Hip & Knee Replacement.
-
Guides 3D-printed from your own scans, so they fit your bone like a glove and line up each cut as planned. See 3D Planning & PSI.
-
Your GP referral, recent x-rays or scans (images and reports), a list of your medications, and details of treatments you've already tried. See Your Appointment.
Trusted resources
These independent sources give more information about knee arthritis and how to manage it.
External links are provided for general information. Dr Arora is not responsible for the content of external websites. Any surgical or invasive procedure carries risks. Before proceeding, you should seek a second opinion from an appropriately qualified health practitioner.

Knee Surgery in Melbourne
If you are experiencing knee pain and would like to discuss your treatment options, contact Dr Varun Arora to schedule a consultation.